Monday, August 12, 2013

Charging Dealers with Murder Following an Overdose Death


Drug selling and buying are considered consensual crimes.  Two people come to an agreement about quantity and price and make an exchange. There is no victim. A merchant who deals in tobacco or alcohol does not belong in a different logical category than a merchant of cocaine, cannabis or opiates. With alcohol or tobacco, after the purchase the responsibility to then use the substance lies with the purchaser, not the seller. If the individual chooses to use the drug in an irresponsible manner, such as operating machinery while intoxicated or otherwise putting others in harm's way, the consequences should lie with the individual. We don't hold liquor stores responsible for drunk drivers or cases of alcohol poisoning, neither should heroin sellers be responsible for overdoses resulting from use of their product.

Similarly the individual should educate themselves about the pharmacological effects of the drug prior to consumption. Just as one should not attempt to drive a car without first learning how to operate an automobile, one should not use drugs without first becoming familiar with their effects. Of course society has put in place regulations on the operating of automobiles, since they can be dangerous in the wrong hands. Unfortunately with illicit drugs it is a free-for-all. Far from drug control, the current system is completely uncontrolled. There are no age restrictions or any prerequisites at all in the illicit drug marketplace outside of cold hard cash. On the supply side there is no standards or quality control. The drug purchased may be something else entirely, or an inert substance. Substances oft injected are not sterile.

Accidental drug overdoses are often tragic, and probably largely avoidable if our drug policies were guided by science instead of hysteria. Nevertheless the drug war machine rolls on, and the bodies continue to stack up. As the crackdown on prescription opioids continues, heroin has been strong comeback, and with it an increase in overdoses.

To respond to the increase in overdoses law enforcement has been moving to charge dealers with additional penalties when a particular sale results in death. The additional penalties are substantial, not that the penalties for selling heroin are anything to laugh at.    


Dealers now being charged in drug overdose deaths

TOMS RIVER, N.J. (AP) — With the number of heroin overdoses skyrocketing nationwide, a growing number of law enforcement agencies are dusting off strict, rarely used drug laws, changing investigatory techniques and relying on technology to prosecute drug dealers for causing overdose deaths.

The aggressive change in tactics comes as more people turn to heroin because of crackdowns on powerful prescription opiate painkillers that make them more expensive and inaccessible. The popular prescription drug OxyContin has also been reformulated to make it difficult to crush and snort, making it less desirable on the street, law enforcement officials said.

Nationwide, the number of people who said they have used heroin in the past year skyrocketed by 66 percent between 2007 and 2011, according to the Substance Abuse and Mental Health Services Administration. The number of people who died of overdoses and had heroin present in their system jumped 55 percent from 2000 to 2010, according to the Centers for Disease Control and Prevention.

Rather than going after lower-level users of heroin, prosecutors are looking to take out dealers and members of the supply chain by connecting them and the drugs they sold to overdose deaths and charging them with laws that carry stiff penalties.

"We're going to be ruthless," said prosecutor Joseph Coronato of Ocean County, N.J., where 75 overdose deaths have occurred this year. "We're looking for long-term prison sentences."

Coronato and other New Jersey prosecutors are employing the state's little-used "strict liability for drug death" statute, a first-degree crime that holds dealers and producers responsible for a user's death and has a 20-year maximum sentence.

He and other prosecutors nationwide are changing the way they investigate overdoses, which were once looked upon as accidents. Detectives are being immediately dispatched when word of an overdose comes in. Paramedics are being told to treat overdoses like crimes. And coroners are being asked to order autopsies and preserve forensic evidence, as proving that a death was caused solely by heroin can be difficult when other opiates, drugs or alcohol are present in a person's system.

"When you go to an overdose death, treat it like a crime scene. Don't treat it like an accident," said Kerry Harvey, the U.S. attorney for eastern Kentucky. He has started prosecuting people who sold both prescription opiates and heroin under a federal law that prohibits the distribution of illicit substances and allows additional penalties for a death.

Technology is another boon to such cases. Prosecutors said cellphones have been instrumental in helping gather enough evidence because people leave behind a trail of text messages and calls.

"People text their dealer and say, 'Get me some horse,'" said Hennepin County, Minn., attorney Mike Freeman, using slang for heroin. "They text back and say, 'Meet me at McDonald's, I have some really good horse.' The guy is dead three hours later."

[...]

Some wonder whether the enforcement efforts are actually going to curtail drug sales. Douglas Husak, a lawyer and professor of philosophy at Rutgers University, said he doesn't think the stricter enforcement will stop people from dealing heroin.

"Heroin distributors are not murderers, and they're not murderers when their customers die from an overdose," said Husak, who has called for decriminalizing drugs.

In New Jersey, officials say heroin has become a scourge across the entire state, prompting Gov. Chris Christie to create a task force on heroin and other opiates. Forty-five percent of the primary drug treatment admissions in 2011 were for heroin, according to the White House Office of National Drug Control Policy.

Mariann Farino's son Raymond died of a heroin overdose in January. Coronato's office charged the man they say sold her son heroin in June.

"Did he stick the needle in my son's arm? No. Did he sell him stuff that was crazy? Yes," she said. "Should he be held partially responsible? Yes."

Ocean County Prosecutor Joseph D. Coronato with packets of confiscated heroin
So let’s put aside the morality or logic of holding dealers responsible for overdoses, there are some very good reasons why this is a bad idea. For one it is doubtful that there will be any deterrent effect from the increase in penalties. The penalty for selling heroin or other opiates is already severe enough to deter most people who might enter the market if prohibition was repealed. There is a point of diminishing returns where additional penalties will have no further deterrent effect. Dealers do not operate on a daily basis expecting to be caught, nor do they expect their clientele to die from their product (it would be bad business to kill your repeat customers). 
Many dealers are dealers in name only. Often they are addicts who support their habit in part by acquiring drugs for others, plus a modest fee. Such people are driven by forces more powerful than criminal law can hope to influence.

How much will the increased penalties cost taxpayers? An added 10 years to a sentence can run into the hundreds of thousands of dollars. As in all aspects of the drug war, this will undoubtedly fall heaviest on the poor and minority communities, exacerbating the already unconscionable racial bias in the US prison system.

Treating overdoses as crime scenes is likely to make the problem of fatal overdoses more likely. Since the increased penalties will have little to no deterrent effect, we can expect the frequency of overdoses to remain unchanged. However people will be less likely to call for help if they are aware that they will be criminally liable, especially if they sold the drugs themselves. This is where "Good Samaritan" laws come into play, where immunity is given in cases of overdoses. Specifics differ and some laws do not grant immunity for selling or for those on probation or in drug court.

What is more important, saving lives or punishing people for using opiates? History has taught us that we cannot do both. Short of a complete repeal of opiate prohibition, methadone, buprenorphine and heroin maintenance has a proven track record of saving lives, improving the health of addicts and the community in general. Naloxone access should be dramatically expanded to get OD kits in the hands of opiate users, and should also be available over-the-counter (OTC). If we are truly serious about ending the "epidemic" of opioid overdoses, this is the way forward (opiates are not infectious particles, this is a metaphorical epidemic).

Thursday, August 1, 2013

Saturday, July 27, 2013

"Glee" Star Cory Monteith

According to the British Columbia Coroner, Cory Monteith, the star of the TV show "Glee", died after taking a toxic combination of heroin and alcohol.

This is another example of how dangerous it is to combine opiates with other CNS depressants (sedatives). Opiates, by themselves, are generally safe, as are most sedatives. It is the combination that is particularly risky.

Still, others speculate that Mr. Monteith was more vulnerable to overdose after recently going through a detox program, because his body was no longer able to tolerate high doses of heroin. There is no evidence indicating he used high doses of heroin in the past or at the time of his death, making this conjecture less plausible. In addition, while it is theoretically possible to die from an overdose of heroin alone, in practical terms this is rare. Only about a quarter of the thousands of heroin-related deaths each year occur as a result of heroin alone. The vast majority of heroin-related deaths -- a whopping 70 percent or more -- are caused by combining heroin with another sedative, usually alcohol. Regrettably, Mr. Monteith too was a victim of this combination. [emphasis added - Ed] 
As a neuropsychopharmacologist who specializes in substance abuse, I find the focus on factors other than this drug combination distracting and irresponsible. Too often in these tragic cases some "experts" emphasize the failures of rehab, rather than providing the drug-using population with practical information that could prevent countless overdose deaths. We are missing an important public health education opportunity to decrease drug-related accidents. 
The Coroner concluded, "there is no evidence to suggest Mr. Monteith's death was anything other than a most-tragic accident." What was not said is that this horrible accident, and the thousands of others that occur each year, could have been prevented if our public health education message clearly focused on the potential dangers associated with the alcohol-heroin combination instead of being preoccupied with blaming rehab and vilifying heroin. 
"Glee" Star Cory Monteith's Death Proves Heroin (Alone) Is Not the Problem by Dr. Carl Hart
I agree with Dr. Hart about educating drug users in overdose prevention, but he is wrong about blaming rehab. While it is absurd to claim Monteith's death was a direct result of his going to rehab, it was almost certainly a contributing factor. 

First Monteith was coerced into rehab by his employer in an "intervention." Apparently his employer found out that Monteith was "using" again and that was sufficient evidence, not whether Monteith's work was actually impaired (which as with tobacco or alcohol should be the standard used, it matters not what drugs an individual consumes but how they behave). Second, the rehab chosen did not use evidence-based practices, but focused on abstinence and the 12-step model. Maia Szalavitz fills us in on the details:
Apparently, these “experts” suggested Eric Clapton’s Crossroads rehab in Antigua, an old-school program that does not “believe in” using medications to treat opioid addiction, despite all the data favoring them as lifesaving for people whose problems involve heroin or painkillers. Murphy implies that Monteith was in another rehab (reportedly Betty Ford) that “didn’t work”—but that after the second program, “all indications were that he’d gone through the Steps.” 
We all know what happened next. Although the intervention did get him into treatment—unlike the one conducted on [Kurt] Cobain, which was followed directly by his suicide—Monteith followed the pattern of the 90 percent of opioid addicts who are coerced into 12-step recovery and denied an adequate period of maintenance treatment: He relapsed.  
He also followed two other predictable and dangerous patterns. 
First, the risk of overdose is highest in the initial few months after being in rehab or any other situation where a period of abstinence has occurred. After a complete detoxification, a person’s tolerance drops precipitously—meaning that the dose they took before treatment without even getting very high may now be potentially fatal. The first two weeks following prison, for example, were shown by one study to carry a greater than 120-fold increased risk of overdose death; that extreme risk elevation holds for whenever the person first uses again after a period without opioids. 
Second, the vast majority of “opioid overdoses”—overdoses involving drugs like heroin or Vicodin—are not accurately characterized by that name. Instead, they are really “opioid mixture overdoses,” typically including an opioid and other depressants like alcohol and/or benzodiazepines like Xanax and Valium. Opioids are the drug that most often makes these mixes turn deadly—but only one third or fewer of so-called opioid overdoses involve those drugs by themselves. 
Monteith took the deadliest possible combination—alcohol and heroin, whose actions to slow breathing are not additive but multiple—at the deadliest possible time. He was likely not informed about the risk because abstinence-focused rehabs typically don’t provide harm reduction advice. He certainly was not provided with maintenance medication like methadone or buprenorphine that can dramatically reduce that risk; he may not even have know that maintenance was an option—just as Cobain was told he could not take any more opioids, even for his chronic pain. Nor, apparently, were Monteith or his loved ones given naloxone, which can reverse opioid overdose, or instructed on how to use it. 
How Addiction Treatment Killed Cory Monteith by Maia Szalavitz
Cory Monteith's death was due to his own actions to be sure. But that does not mean that we, as a society, have not contributed to it with our drug policies. Had heroin been legal and pure, and accurate drug information was covered in grade school in place of counterproductive anti-drug "education", perhaps it would be widely known not to mix opiates with sedatives.

Had opiates been legal, I highly doubt his employer would have been able to coerce Monteith into rehab. The very notion of staging an "intervention" over non-problematic opiate use would seem as absurd as staging an intervention over occasional alcohol drinking. If Monteith's opiate use did indeed become problematic and interfere with his work, he should have at least have been given the option of maintenance medicines. Szalavitz also addresses this in the same article cited above:
In no other type of treatment are FDA-approved medications seen as appropriate to withhold—without even informing the patient of their existence. No cancer center in the US provides only chemo while refusing to inform patients about radiation treatment or putting it down as something “we don’t believe in here” because it is “cheating” rather than “real recovery.” But the equivalent is done in addiction treatment—even for celebrities—every day. If we don’t want to keep losing patients, we’ve got to actually treat addiction like a disease, by providing evidence-based treatment, not just repeating faith-based philosophies.
Monteith's death, like thousands of others, could have been prevented if our drug policies approached drugs in a rational way. Instead we get vilification of drugs and the people who use them. Meanwhile the body count grows ever higher.

Saturday, July 20, 2013

Opioid Antagonists: Naloxone and Naltrexone

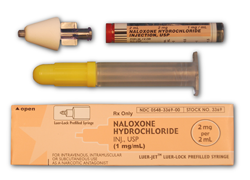
The effects of opioids are primarily due to their action on the mu opioid receptor. Molecules that interact with this receptor can be classified into three primary types, full agonists, partial agonists and antagonists. Full agonists such as morphine or methadone activate the receptor in a dose dependent manner. Partial agonists also activate the receptor, but the activation reaches a plateau and will not respond to increases in dosage. Finally antagonists such as naloxone bind to the receptor, but do not activate it at all.


The two most commonly used opioid antagonists are naloxone and naltrexone. Both are competitive antagonists, which means they work by competing for the receptor's binding site. The strength of the bond between the ligand (drug) and the receptor is known as the affinity. Molecules with higher affinity for the receptor will replace those with lower affinity. Naloxone has a higher affinity for the mu opioid receptor than morphine, when administered it will replace the morphine bound to the receptor. Because naloxone is an antagonist, the receptor will deactivate completely reversing the effects of the morphine.


Both naltrexone and naloxone can be described as substituted derivatives of oxymorphone. The tertiary amine methyl-substituent is replaced with a longer chain of carbon atoms (an allyl group). With naloxone the N-methyl group of oxymorphone is substituted with an N-prop-2-enyl group, with naltrexone this substitution is with an N-cyclopropylmethyl group. The name naloxone has been derived from N-allyl and oxymorphone.

While both antagonists have high oral bioavailability, they both undergo extensive first-pass metabolism. Up to 98% of naloxone is metabolized to an inactive metabolite, and for this reason it must be administered as an injection or intranasal spray. Naltrexone is metabolized to 6-β-naltrexol, which is an active metabolite also acting as an antagonist at the mu receptor. While naloxone is used primarily as an emergency antidote to opioid overdoses, naltrexone has been used as a medication to treat alcoholism and opioid addiction.


Pharmacokinetics

"When naloxone hydrochloride is administered intravenously the onset of action is generally apparent within two minutes; the onset of action is only slightly less rapid when it is administered subcutaneously or intramuscularly. The duration of action is dependent upon the dose and route of administration of naloxone hydrochloride. Intramuscular administration produces a more prolonged effect than intravenous administration. The requirement for repeat doses of naloxone hydrochloride, however, will also be dependent upon the amount, type and route of administration of the narcotic being antagonised. Following parenteral administration naloxone hydrochloride is rapidly distributed in the body. It is metabolised in the liver, primarily by glucuronide conjugation and excreted in the urine. In one study the serum half-life in adults ranged from 30 to 81 minutes (mean 64 ± 12 minutes). In a neonatal study the mean plasma half-life was observed to be 3.1 ± 0.5 hours."
-Naloxone Data Sheet (New Zealand)

"Naltrexone Hydrochloride is a pure opioid receptor antagonist. Although well absorbed orally, naltrexone is subject to significant first pass metabolism with oral bioavailability estimates ranging from 5 to 40%. The activity of naltrexone is believed to be due to both parent and the 6-β-naltrexol metabolite. Both parent drug and metabolites are excreted primarily by the kidney (53% to 79% of the dose), however, urinary excretion of unchanged naltrexone accounts for less than 2% of an oral dose and faecal excretion is a minor elimination pathway. The mean elimination half-life (T-1/2) values for naltrexone and 6-β-naltrexol are 4 hours and 13  hours, respectively. The elimination half-life and time to maximum concentration are dose-independent.  Naltrexone and 6-β-naltrexol are dose proportional in terms of AUC and Cmax over the range of 50 to 200 mg and there is no significant accumulation after 100 mg daily doses."
-Naltrexone Data Sheet (New Zealand)

Responding to an opiate overdose

Most overdoses are the result of mixing opiates with central nervous system depressants. Although naloxone only works on opioids, it is the synergism of the drug combo that causes the overdose. Removing the opioid component only will usually restore respiratory function. Opiate users should practice assembling the naloxone kit so as to be efficient in case of an emergency. If someone has stopped breathing every minute matters, combined with the stress and adrenaline of the emergency you don't want to have to take time out to read an instruction manual. Since naloxone overdose kits have been introduced in the US, over 10,000 lives have been saved by non-emergency persons (the friends and family of drug users).

If the individual has stopped breathing:

Do rescue breathing for a few quick breaths, then administer the naloxone. Depending on if the naloxone is administered as an injection or intranasally, it may take a few minutes to take effect. If there is no effect after 3-5 minutes, administer another dose of naloxone.

If the naloxone does not work after the second application, something is wrong. Naloxone may not work if:

1. The overdose is not due to opioids.
2. The opioid causing the overdose has a higher affinity for the mu receptor than naloxone, which can happen with some synthetic opioids (such as buprenorphine or fentanyl and its analogs).
3. Too much time has lapsed and the heart has stopped.


"Naloxone only lasts between 30 – 90 minutes, while the effects of the opioids may last much longer. It is possible that after the naloxone wears off the overdose could recur. It is very important that someone stay with the person and wait out the risk period just in case another dose of naloxone is necessary. Also, naloxone can cause uncomfortable withdrawal feelings since it blocks the action of opioids in the brain. Sometimes people want to use again immediately to stop the withdrawal feelings. This could result in another overdose. Try to support the person during this time period and encourage him or her not to use for a couple of hours."
Administer Naloxone Overdose Response from Harm Reduction Coalition 

Further Reading:

Community-Based Opioid Overdose Prevention Programs Providing Naloxone — United States, 2010
Morbidity and Mortality Weekly Report (MMWR)
February 17, 2012 / 61(06);101-105 [Link]


Understanding Naloxone, Harm Reduction Coalition

Tuesday, July 16, 2013

Drug Prohibition and Human Rights

The War on Drugs is causing human rights violations on a global scale.

All over the world, people are subjected to police mistreatment, harassment and arbitrarily arrest simply for their choice of intoxicant. Many are subject to involuntary "treatment", which amounts to little more than prison labor camps. The "patients" (inmates) are either unpaid, or paid below the minimum wage and then nickel-and-dimed with administrative fees. Resistance is met with savage beatings, torture, sexual abuse and increased time added to their "rehabilitation". Most "patients" are forced into treatment without judicial overview or opportunity for appeal. Drug treatment, when present at all, is not evidence-based. (One example includes having the "patients" chant "Healthy!Healthy!Healthy!").

One product of these labor camps is shelled cashews and the US is an importer. If you buy shelled cashews in the US it is quite possible they were shelled by a fellow opiate user enslaved by the state. As part of their "treatment", the drug users are given quotas to fill. Failure to meet the quotas are met with severe punishment.

Opiophobia and the war on drugs is also the driving force behind the inhumane treatment of pain. Third world countries are especially hard hit, the supply does not come anywhere near the levels necessary to meet the demand. This is inexcusable, morphine is cheap and easy to produce. It is also remarkably safe when used properly. There is no maximum dose. It is also relatively safe, if one was to accidentally take double the expected dose, death or organic damage would be very unlikely. Whereas if one was on the highest recommended daily dosage of acetaminophen, and accidentally doubled the dosage serious liver damage may result. Addiction in patients taking opiates for pain is actually uncommon. Even young children and terminal patients are not excepted from their torments. And really, even if aggressive treatment with opiates did result in addiction, does it really matter when the person is dying? Is the risk of addiction sufficient to justify forcing someone to live in agony?

Criminalizing drug use itself undermines our basic human right to autonomy and privacy, according to Human Rights Watch. I would also add that it violates our freedom of medicine, and the right to self-medicate. Since the US incarcerates more of its citizens than any other country in the world, largely for drug "crimes", the US itself is one of the world's greatest human rights violators. Government intransigence on the issue of harm reduction is causing an epidemic of HIV and hepatitis infections among injection drugs users, violating their right to a high standard of health.


From Human Right's Watch
(Antigua) – National drug control policies that impose criminal penalties for personal drug use undermine basic human rights, Human Rights Watch said today. To deter harmful drug use, governments should rely instead on non-penal regulatory and public health policies. The 43rd General Assembly of the Organization of American States, taking place in Antigua, Guatemala from June 4 to 6, 2013, will focus on drug control policy in the Americas.

Governments should also take steps to reduce the human rights costs of current drug production and distribution policies, Human Rights Watch said. Among the steps should be reforming law enforcement practices and exploring alternatives for legal regulation that would reduce the power of violent criminal groups.
[...]
Subjecting people to criminal sanctions for the personal use of drugs, or for possession of drugs for personal use, infringes on their autonomy and right to privacy, Human Rights Watch said. The right to privacy is broadly recognized under international law, including in the International Covenant on Civil and Political Rights and the American Convention on Human Rights. Limitations on autonomy and privacy cannot be justified unless they meet the criteria for any restriction of a basic right, namely legitimate purpose, proportionality, necessity, and non-discrimination.

While protecting health is a legitimate government purpose, criminalizing drug use to protect people from harming themselves does not meet the criteria of necessity or proportionality. Governments have many non-penal options to reduce harm to people who use drugs, including offering substance abuse treatment and social support.

Human Rights Watch research around the world has found that the criminalization of drug use has undermined the right to health. Fear of criminal penalties deters people who use drugs from using health services and treatment, and increases their risk of violence, discrimination, and serious illness. Criminal prohibitions have also impeded the use of drugs for legitimate medical research, and have prevented patients from accessing drugs for palliative care and pain treatment.

“There are many steps that governments can and should take to deter, prevent and remedy the harmful use of drugs,” Vivanco said. “But they shouldn’t do it by punishing the people whose health they are trying to protect.”

Governments have a legitimate interest in protecting third parties from harm resulting from drug use, such as driving under the influence, Human Rights Watch said. They may impose, consistent with human rights, proportionate criminal penalties on behavior that occurs in conjunction with drug use if that behavior causes or seriously risks harm to others.

With respect to drug use by children, governments have obligations to take appropriate legislative, administrative, social, and educational measures to protect children from the illicit use of drugs. Governments should not impose criminal penalties on children for drug use or possession, Human Rights Watch said.

“When someone under the influence of drugs does something that could harm others, whether it’s driving a car or endangering a child through neglect, criminal sanctions may be entirely appropriate, just as they are when people use alcohol in a way that endangers others,” said Vivanco. “However, the penalty is not for drug use alone but for engaging in activity that could endanger others while under the influence of drugs.”
Americas: Decriminalize Personal Use of Drugs
The article goes on to discuss human rights violations caused by the production and distribution of illicit drugs, and the reactionary role of the UN International Narcotics Control Board.

Below are specific reports from Human Rights Watch. I have grouped them into three categories: pain medicine access, abuse in the name of drug treatment, and general policy and HIV response.


Pain Treatment and Access to Medicine

Global State of Pain Treatment Access to Medicines and Palliative Care. June 3, 2011

This 128-page report details the failure of many governments to take even basic steps to ensure that people with severe pain due to cancer, HIV, and other serious illnesses have access to palliative care, a health service that seeks to improve quality of life. As a result, millions of patients live and die in great agony that could easily be prevented, Human Rights Watch said.


“Please, do not make us suffer any more…” Access to Pain Treatment as a Human Right. March 3, 2009
In this 47-page report Human Rights Watch said that countries could significantly improve access to pain medications by addressing the causes of their poor availability. These often include the failure to put in place functioning supply and distribution systems; absence of government policies to ensure their availability; insufficient instruction for healthcare workers; excessively strict drug-control regulations; and fear of legal sanctions among healthcare workers.

Human Rights Abuses in the Name of Treatment


Torture in the Name of Treatment Human Rights Abuses in Vietnam, China, Cambodia, and Lao PDR. July 24, 2012
More than 350,000 people identified as drug users are held in compulsory drug "treatment" centers in China and Southeast Asia. Detainees are held without due process for periods of months or years and may be subjected to physical and sexual abuse, torture, and forced labor. International donors and UN agencies have supported and funded drug detention centers, while centers have systematically denied detainees access to evidence-based drug dependency treatment and HIV prevention services. "Torture in the Name of Treatment," summarizes Human Rights Watch’s findings over five years of research in China, Cambodia, Vietnam, and Lao PDR.

“Skin on the Cable” The Illegal Arrest, Arbitrary Detention and Torture of People Who Use Drugs in Cambodia. January 25, 2010
In this 93-page report Human Rights Watch documents detainees being beaten, raped, forced to donate blood, and subjected to painful physical punishments such as "rolling like a barrel" and being chained while standing in the sun. Human Rights Watch also reported that a large number of detainees told of receiving rotten or insect-ridden food and symptoms of diseases consistent with nutritional deficiencies.

“Where Darkness Knows No Limits” Incarceration, Ill-Treatment and Forced Labor as Drug Rehabilitation in China. January 7, 2010
This 37-page report based on research in Yunnan and Guangxi provinces, documents how China's June 2008 Anti-Drug Law compounds the health risks of suspected illicit drug users by allowing government officials and security forces to incarcerate them for up to six years. The incarceration is without trial or judicial oversight. The law fails to clearly define mechanisms for legal appeals or the reporting of abusive conduct, and does not ensure evidence-based drug dependency treatment.

The Rehab Archipelago Forced Labor and Other Abuses in Drug Detention Centers in Southern Vietnam. September 7, 2011
The 121-page report documents the experiences of people confined to 14 detention centers under the authority of the Ho Chi Minh City government. Refusing to work, or violating center rules, results in punishment that in some cases is torture. Quynh Luu, a former detainee who was caught trying to escape from one center, described his punishment: "First they beat my legs so that I couldn't run off again... [Then] they shocked me with an electric baton [and] kept me in the punishment room for a month."

Somsanga’s Secrets Arbitrary Detention, Physical Abuse, and Suicide inside a Lao Drug Detention Center. October 11, 2011
This report examines conditions in the Somsanga Treatment and Rehabilitation Center, which has received a decade of international support from the United States, the United Nations, and other donors. Detainees are held without due process, and many are locked in cells inside barbed wire compounds. Former detainees told Human Rights Watch that they had been held for periods of three months to more than a year. Police and guards are a constant presence, and those who try to escape may be brutally beaten.

An Unbreakable Cycle Drug Dependency Treatment, Mandatory Confinement, and HIV/AIDS in China’s Guangxi Province December 9, 2008
In China, illicit drug use is an administrative offense and Chinese law dictates that drug users “must be rehabilitated.” In reality, police raids on drug users often drive them underground, away from methadone clinics, needle exchange sites, and other proven HIV prevention services. And every year Chinese police send tens of thousands of drug users to mandatory drug treatment centers, often for years, without trial or due process.
This report finds that most mandatory treatment centers, while ostensibly meant to provide drug treatment, do not actually offer forms of drug dependence treatment internationally recognized as effective. Mostly, drug users are forced to work or to spend their days in crowded cells little different from prisons.


Barred from Treatment Punishment of Drug Users in New York State Prisons. March 24, 2009
In this 53-page report, Human Rights Watch found that New York prison officials sentenced inmates to a collective total of 2,516 years in disciplinary segregation from 2005 to 2007 for drug-related charges. At the same time, inmates seeking drug treatment face major delays because treatment programs are filled to capacity. When sentenced to segregation, known as "the box," inmates are not allowed to get or continue to receive treatment. Conditions in the box are harsh, with prisoners locked down 23 hours a day and contact with the outside through visitors, packages, and telephone calls severely restricted.

Public Policy and HIV

Rehabilitation Required Russia’s Human Rights Obligation to Provide Evidence-based Drug Dependence Treatment. November 8, 2007
In this 110-page study, Human Rights Watch found that the treatment offered at state drug treatment clinics in Russia was so poor as to constitute a violation of the right to health. The report concluded that drug dependent people in Russia who want to overcome their dependence are left virtually to their own devices in their battle with this serious and chronic disease.


Injecting Reason Human Rights and HIV Prevention for Injection Drug Users. September 9, 2003
Government interference with sterile syringe programs is thwarting HIV prevention efforts in California. State laws and local enforcement are preventing drug users from obtaining the sterile syringes they need to protect themselves from HIV. This 61-page report documents police stopping, arresting, and harassing participants in needle exchange programs established by some California counties under state law. Even where needle exchange programs are legal, police remain authorized to arrest program participants under an antiquated law prohibiting the possession of “drug paraphernalia.” Over a quarter of new AIDS cases in the United States can be traced to infected syringes. Sharing syringes is also a major risk factor in the spread of hepatitis B and C. California is home to nearly one eighth of reported AIDS cases in the United States. The Human Rights Watch report recommends legalization of needle exchange programs and nonprescription pharmacy sales of syringes. It also calls on police departments to cease stops and seizures of participants in clean needle programs, a practice courts have recently prohibited in Connecticut, Massachusetts and New York.

Not Enough Graves The War on Drugs, HIV/AIDS, and Violations of Human Rights. July 8, 2004
This 60-page report provides fresh evidence of extrajudicial killings, arbitrary arrests and other human rights violations by Thai authorities. The report contains first-hand testimony from relatives of people killed during the drug war, as well as drug users who endured beatings, forced confessions and arbitrary arrests at the hands of Royal Thai Police. The government's anti-drug campaign has resulted in as many as 3,000 killings and has driven drug users underground and away from lifesaving HIV prevention services.

Abusing the User: Police Misconduct, Harm Reduction and HIV/AIDS in Vancouver. May 7, 2003
An anti-drug crackdown by the Vancouver Police Department has driven injection drug users away from life-saving HIV prevention services, raising fears of a new wave of HIV transmission in the city that is already home to the worst AIDS crisis in the developed world, said Human Rights Watch. In a 25-page report released today, “Abusing the User: Police Misconduct, Harm Reduction and HIV/AIDS in Vancouver,” Human Rights Watch documents instances of unnecessary force and mistreatment, arbitrary arrest, and other intimidation and harassment of drug users as part of a campaign commonly referred to as Operation Torpedo. The crackdown began on April 7 in the city’s impoverished Downtown Eastside neighborhood. Though drug traffickers are the ostensible target, drug users not charged with selling drugs have been driven to places where health workers cannot reach them to ensure access to sterile syringes and other HIV prevention services.

Courage in the Face of Death: The Thai Drug Users’ Network. July 13, 2004
Thailand enjoys an international reputation as a “best practice” model in the fight against AIDS principally because of its “100 percent condom” campaign in the 1990s. This campaign engaged sex workers with the clear recognition that they were part of the solution to a growing AIDS epidemic. Drug users have not enjoyed the same recognition in Thailand.

Friday, May 31, 2013

Exploring the Heroin Overdose Myth

Most fatal overdoses attributed to heroin are not actually the result in taking too large a dose. Heroin overdoses are largely a myth.


What causes people to overdose on heroin? The conventional wisdom states that because heroin users do not know the purity of the drug they are consuming, they misjudge the strength of the dose. If only users knew the exact dosage, they wouldn't overdose.
    This is largely a myth. The Consumers Union Report on Licit and Illicit Drugs exposed this myth back in 1972:
But alas, the two standard precautions against overdose--- warnings against taking too much and administration of an antidote--- are in fact wholly ineffective in the current crisis, for the thousands of deaths attributed to heroin overdose are not in fact due to heroin overdose at all. The evidence falls under three major rubrics.
(1) The deaths cannot be due to overdose.
(2) There has never been any evidence that they are due to overdose.
(3) There has long been a plethora of evidence demonstrating that they are not due to overdose.
Why these deaths cannot be due to overdose. The amount of morphine or heroin required to kill a human being who is not addicted to opiates remains in doubt but it is certainly many times the usual dose (10 milligrams) contained in a New York City bag. "There is little accurate information," Drs. A. J. Reynolds and Lowell. Randall report in Morphine and Allied Drugs (1967). "The figures that have been reported show wide variation." This ignorance no doubt stems from the rarity of morphine or heroin overdose deaths. The amounts of morphine or heroin needed to kill a nonaddict have been variously estimated at 120 milligrams (oral), 200 milligrams, 250 milligrams, and 350 milligrams - though it has also been noted that nonaddicts have survived much larger doses. 
The best experimental evidence comes from Drs. Lawrence Kolb and A. G. Du Mez of the United States Public Health Service; in 1931 they demonstrated that it takes seven or eight milligrams of heroin per kilogram of body weight, injected directly into a vein, to kill unaddicted monkeys. On this basis, it would take 500 milligrams or more (50 New York City bags full, administered in a single injection) to kill an unaddicted human adult.
[...]
Dr. Helpern's associate, Deputy Chief Medical Examiner Baden, went on to further discredit the already implausible overdose theory at a joint meeting of two American Medical Association drug-dependency committees held in Palo Alto, California, in February 1969.
"The majority of deaths," Dr. Baden told the AMA physicians, "are due to an acute reaction to the intravenous injection of the heroin-quinine-sugar mixture. This type of death is often referred to as an 'overdose,' which is a misnomer. Death is not due to a pharmacological overdose in the vast majority of cases."  
At the same AMA committee meeting and at a meeting of the Medical Society of the County of New York, Dr. Baden cited six separate lines of evidence overturning the "heroin overdose" theory. 
First, when the packets of heroin found near the bodies of dead addicts are examined, they do not differ from ordinary packets. "No qualitative or quantitative differences" are found. This rules out the possibility that some incredibly stupid processor may have filled a bag with pure heroin instead of the usual adulterated mix.
Second, when the syringes used by addicts immediately before dying are examined, the mixture found in them does not contain more heroin than usual.
Third, when the urine of addicts allegedly dead of overdose is analyzed, there is no evidence of overdose.
Fourth, the tissues surrounding the site of the fatal injection show no signs of high heroin concentration.
Fifth, neophytes unaccustomed to heroin rather than addicts tolerant to opiates would be expected to be susceptible to death from overdose. But "almost all of those dying" of alleged overdose, Deputy Chief Medical Examiner Baden reported, "are long-term users."
Sixth, again according to Dr. Baden, "addicts often 'shoot' in a group, all using the same heroin supply, and rarely does more than one addict die at such a time." 

So if heroin overdoses are not truly due to taking too much heroin, what is killing heroin users?

1. Mixing opiates with other central nervous system depressants, especially alcohol and benzodiazepines.

The depressant effect of opiates on breathing can be countered by conscious effort and opiates rarely result in a loss of consciousness. When combining opiates with CNS depressants, the drugs work synergistic ally to depress breathing, doses which may be well tolerated when taken alone can be fatal when combined. If an individual stops breathing in the presence of others an overdose can be avoided by waking the person up. Alcohol and benzodiazepines cause a loss of consciousness which preclude this possibility.

The combination of opiates and other CNS depressants account for at least half of all overdoses attributed to opiates, and in all probability are responsible for more than 50%. Educating people not to mix depressants with opiates would do more than any other preventative, educational campaign. It would certainly save more lives than just saying don't use heroin.

2. Deliberate Overdosing. Suicide is a major contributor to the overdose statistics.

Poor mental health and feelings of hopelessness are associated with overdose. Opiate addicts are far more likely to attempt suicide, four times as likely for men and eleven times as women. Overdose suicides are almost certainly under reported, so this rate may be much higher.
     Unless the evidence for suicide is overwhelming most overdoses are considered accidental.  Establishing the number of suicide-overdoses is difficult.  One method involves asking persons who survived an overdose if it was intentional, then extrapolating this rate to those who died from an overdose.  Studies done in the UK indicate that up to a third of overdoses may have been intentional.  One of the few prospective studies followed British opiate and cocaine addicts notified by doctors.  The rate of confirmed suicides was 4 times higher than the general population for men and 11 times for women; 45% used an overdose of drugs as the method.  In British studies of persons on methadone deliberate, non-fatal overdose is twice as common as accidental.  A London study of opiate injectors not in treatment found that 1 in 10 overdoses is deliberate.  It is hard to determine the number of overdoses that are intentional, but it seems that somewhere around 10-30% are deliberate.

3. Fluctuations in tolerance.

Addicts are more likely to OD when their tolerance is at its lowest. Users are most at risk for an overdose when they drop out (or are kicked from) an opioid maintenance program, after a period of forced abstinence  (usually due to incarceration), or after discharge from a detoxification hospital. This is more of a risk factor than a cause, but I included it in the list.

4. Homelessness and Street Use

An oft overlooked aspect of heroin use involves the mindset of the user and the environment where he/she is using. Opiate tolerance is not a purely physiological phenomenon, tolerance is also situation specific. Most regular opiate users have a ritual of preparation prior to ingesting the drug. Situation-specific tolerance is also a piece of the opiate overdose mystery:
The fatal consequence of the heroin injection may have been caused by the failure in the action of conditioned tolerance. As the figure shows, when a conditioned place preference arises, the user has to take a bigger dose each time to achieve the same effect as the user who does not have the opportunity for secondary conditioning with environmental stimuli since he or she constantly changes the place where the drug is taken [6]. When the drug is taken in a strange environment the conditioned tolerance does not operate since the organism is not "expecting" the drug. The end result is that the otherwise accustomed dose leads to an overdose and thereby to death. This is why the term "overdose" is misleading since the quantity taken was not greater than other doses taken without fatal complications
A case report: Pavlovian conditioning as a risk factor of heroin 'overdose' death. József Gerevich1, Erika Bácskai1, Lajos Farkas and Zoltán Danics. [Link]


Heroin concentration levels in a case A after conditioning in an accustomed place (A1) and in a new place (A2), and in a case B without conditioning.


Most "overdoses" involving opiates are chalked up to the use of opiate drugs regardless of the circumstances around the death (polydrug use, ect.)  This is well documented and known among those that care about the lives of users.  Unfortunately most people simply do not care about users and medical examiners readily attribute the cause of death to opiate drugs regardless of the toxicology.

Putting these factors together it becomes clear that drug prohibition itself contributes to overdoses among opiate users. Opiate prohibition causes inflated prices, users may add other drugs to augment the expensive opiates. Without prohibition, the cycle of addicts coming in and out of jails, prisons, detoxes and rehabs would come to an end. Each time an addict has their tolerance lowered they are at increased risk for an overdose.

The constant drug war propaganda in the media portrays opiate addicts, and especially heroin addicts, in an extremely negative light. Addicts are stereotyped as dangerous criminals, out of control and in need of rehabilitation. The uniformly negative view of addicts, combined with blatant stigma and discrimination (discrimination even written into the law), causes most addicts to hide their use. The situation today is not unlike how homosexuality was treated in the early 20th century. Today most addicts remain in the closet, for very good reasons. Being constantly reminded that one is both sick and a criminal (two charges also once leveled against homosexuals), takes its toll. The rate of suicide among homosexuals was also high during the peak periods of homophobia.

The artificially high cost of black market opiates causes many addicts to fall into abject poverty. Not only does homelessness make hygiene difficult, but it contributes to "street use" (use outside of one's usual place of consumption, such as a public bathroom). This contributes to a lowering of situation specific tolerance, further putting the user at risk of an overdose.

More on this topic to come.

References and Further Reading:

The Consumers Union Report on Licit and Illicit Drugs by Edward M. Brecher and the Editors of Consumer Reports Magazine, 1972
Chapter 12. The "heroin overdose" mystery and other occupational hazards of addiction [Link]

The Persistent, Dangerous Myth of Heroin Overdose by Stanton Peele [Link]

Drug and Alcohol Findings Issue 4 2000. Overdosing on opiates Part I Causes by David Best et al. [Link]

Drug and Alcohol Findings Issue 5 2001.Overdosing on opiates Part II Prevention by David Best et al. [Link]

Reducing heroin ‘overdose’ death risk [Link]

Siegel S, Hinson RE, Krank MS, McCully J: Heroin "overdose" death: Contribution of drug-associated environmental cues. Science 1982, 216:436-437

Sunday, May 26, 2013

Are Psychosocial Interventions with Addicts Worthless?

It is often said that addicts require counseling in addition to maintenance drugs for the treatment of opioid dependence. This review of over 4000 patients cast doubt on that assertion. It would appear that opioid addicts simply require their drug supply. More evidence that ending drug prohibition would cause the problem of opioid addiction to cease to be a social problem.


Psychosocial combined with agonist maintenance treatments versus agonist maintenance treatments alone for treatment of opioid dependence. Amato L, Minozzi S, Davoli M, Vecchi S.
Cochrane Database Syst Rev. 2011 Oct 5;(10):CD004147. doi: 10.1002/14651858.CD004147.pub4
[Link]

MAIN RESULTS:
35 studies, 4319 participants, were included. These studies considered thirteen different psychosocial interventions. Comparing any psychosocial plus any maintenance pharmacological treatment to standard maintenance treatment, results do not show benefit for retention in treatment, 27 studies, 3124 participants, RR 1.03 (95% CI 0.98 to 1.07), abstinence by opiate during the treatment, 8 studies, 1002 participants, RR 1.12 (95% CI 0.92 to 1.37), compliance, three studies, MD 0.43 (95% CI -0.05 to 0.92), psychiatric symptoms, 3 studies, MD 0.02 (-0.28 to 0.31), depression, 3 studies, MD -1.70 (95% CI -3.91 to 0.51) and results at the end of follow up as number of participants still in treatment, 3 studies, 250 participants, RR 0.90 (95% CI 0.77 to 1.07) and participants abstinent by opioid, 3 studies, 181 participants, RR 1.15 (95% CI 0.98 to 1.36). Comparing the different psychosocial approaches, results are never statistically significant for all the comparisons and outcomes.